Category Archives: Immunology

Allergies and School/Nursery

Once a child starts school/nursery, the risk of reactions (and anxiety about potential reactions) starts to ramp up. Obviously, this is because other people are responsible for sourcing and providing food, often to many different children at once.

In the UK, probably 1 pupil with a food allergy in every classroom.

“Schools are the most common setting for severe allergic reactions, with 18% of all food allergy reactions and 25% of first-time anaphylactic episodes occurring there. Fatal anaphylaxis in children occurs more often in schools than any other setting” [Benedict Blythe Foundation “Keeping the promise” document] – but this data appears to be from old US studies. From my data (19/8/26) I see 4 mentions of anaphylaxis related to school in the last 2 years (about 10% of all anaphylaxis reports) – but half of these were actually related to after school.

Miranda Crilley (CHI Dublin) reported on 521 food allergic children attending school/nursery, and found a 4.5/5% annual rate of reactions in schools. Half of nursery reactions due to milk.  6 of 7 nut reactions in schools with nut bans! 33% of children had not provided copies of their allergy action plans to the school. 22% or the reactions were judged as anaphylaxis, none received adrenaline from school staff. “Promoting milk/egg tolerance in infancy would prevent”.

Scottish government policy on healthcare needs in schools (2017): talks about “coordinated support plans” as well as individual health plans and child plans. Talks about local strategic joint arrangements between NHS boards and educational authority. Inhalers and defibrillators (!) specified.  “General awareness raising training of common conditions should be provided… for example, asthma, diabetes, epilepsy, eczema and allergic reactions (including anaphylaxis).”

Specific school arrangements may include:

  • who in the school accepts responsibility, in principle, for supporting the healthcare needs of children and young people in the school;
  • who is responsible in school for staff training in regard to supporting healthcare needs and administering medication;
  • emergency procedures at the school including a main point of contact in the school health team [defined how?];
  • details of any centrally held inhalers; anaphylaxis auto-injectors; the storage of and access to medication in the school;
  • who is responsible for ensuring the safety of children and young people’s self-management of their medical conditions;
  • the arrangements in place to ensure that staff are informed and kept up to date about children and young people’s healthcare needs at school.

First do no harm – parents tend to overestimate risk of anaphylaxis, whereas there are clear consequences to restricting the child’s ability to sit with other children at snack/meal times, or restricting the food choices of other children.

School Allergy Care

https://www.rightdecisions.scot.nhs.uk/school-allergy-care/ from George Raptis in Glasgow is a great resource.

Recommends that an Allergy management policy should be in place (even if incorporated into wider medical conditions policy) even if no currently diagnosed allergic children [quotes 25% undiagnosed reaction rate in school] – cites 2017 Government supporting CYP with healthcare needs document:

  • Procedure for identifying pupils with allergy and high risk pupils.
  • Details on developing Individual Healthcare Plans.
  • Protocol for storage and access to emergency medication – emergency kits.*
  • Arrangements for staff training.
  • Policies and arrangements on Preventative Measures.
  • Details on the administration of medications.
  • Protocol for the emergency response to anaphylaxis.
  • The rights, roles and responsibilities of staff, pupil(s) and parent/ carer(s).

Highlights breakfast clubs and after school as under the remit of schools (and school trips, too).

Refers to EAACI/DOH guidelines:

  1. Allergy lessons as part of curriculum
  2. Education for all school staff in preventing cross contamination of allergens during handling, preparation and serving of food.
  3. Emergency medication stored in school for pupils with allergies.
  4. Distribution of menus to parents/carers and pupils with the 14 allergens listed
  5. (a full ingredients list should be made available upon request)
  6. Supervision during meal times.
  7. Allergen free areas, where there may be a high risk of allergen exposure, e.g. canteen or cooking classes.
  8. Clear allergen labelling of all meals, drinks and snacks in the canteen.
  9. Labelling individual cups/ bottles/ containers with children’s names.
  10. No food sharing policy.
  11. No eating utensil sharing policy.
  12. Routine Cleaning (with warm soapy water and disinfectant) of tables, floors and food preparation areas, especially after meal times.
  13. Encourage hand-washing after meals/ snacks.
  14. Discuss with parents/carers and obtain their permission before giving food treats to pupils with allergies (e.g. birthday parties or special events).
  15. Risk assessments completed for school trips, exchanges and excursions.
  16. No eating policy on school buses.

“Things to consider:” specific food bans as not equitable; potential for stigma and restricted opportunities (“can’t guarantee”).

Discusses indemnity/insurance incl private schools. Getting insurance will usually require training and allergy plans as a condition!

Food also becomes an issue at special school events (festivals, shows, fundraisers), in art classes, as rewards/treats…

Nut bans

Probably better to increase allergy awareness (which varies widely) than rely on classroom or school-wide bans [Dave Stukus editorial]. Here is a podcast video I did with Anaphylaxis UK about nut bans in schools – https://youtu.be/1TcMqMe3Q_4?si=1rQ5AgA5QguO_F0I

And another about how schools can become more allergy aware – because it’s not just about nuts – https://youtu.be/JHnmcmUP6Cs?si=FgjhoxcOdMoEb7eS. George Raptis has shown how school allergy training (in NW England) can improve allergy awareness, not just confidence in managing an allergic emergency.

Benedict Blythe – School allergy code

https://theallergyteam.com/schools-allergy-code/ from the Allergy Team plus Benedict Blythe foundation.

Checklist, register, trust mark!

2 pages (plus separate checklist). 4 points – 

  1. Whole school approach – not just catering/medical – skills (risk reduction, inclusion, first aid); allergy awareness in classroom activities [curriculum?]
  2. Communicate clearly – Allergy and Anaphylaxis Policy (no template!) – (accessible), – and designated allergy lead.  IHPs (individual health plans)
  3. Clear governance and risk management – designated lead, other roles/responsibilities. Allergies in every risk assessment
  4. Readiness to respond – 2 in date AAIs for those prescribed them. Hold spare pens in obvious place. Annual risk reduction and ana training. “Ana emergency response plan” [in allergy policy, presumably?], rehearse

Schools allergy code backed by Dept of Education in England.

React report

Data from 2000 English schools, about 10%.

Assessed 4 allergy safe guards: a specific allergy policy, spare pens, allergy training for staff, incident reporting.

69% did not have all recommended safe guards in place. “Pot luck whether your local school has medication, communication and education relating to allergy made available to teachers”. But commented on how well schools are managing despite “seeming lack of guidance, training and funding from government”.
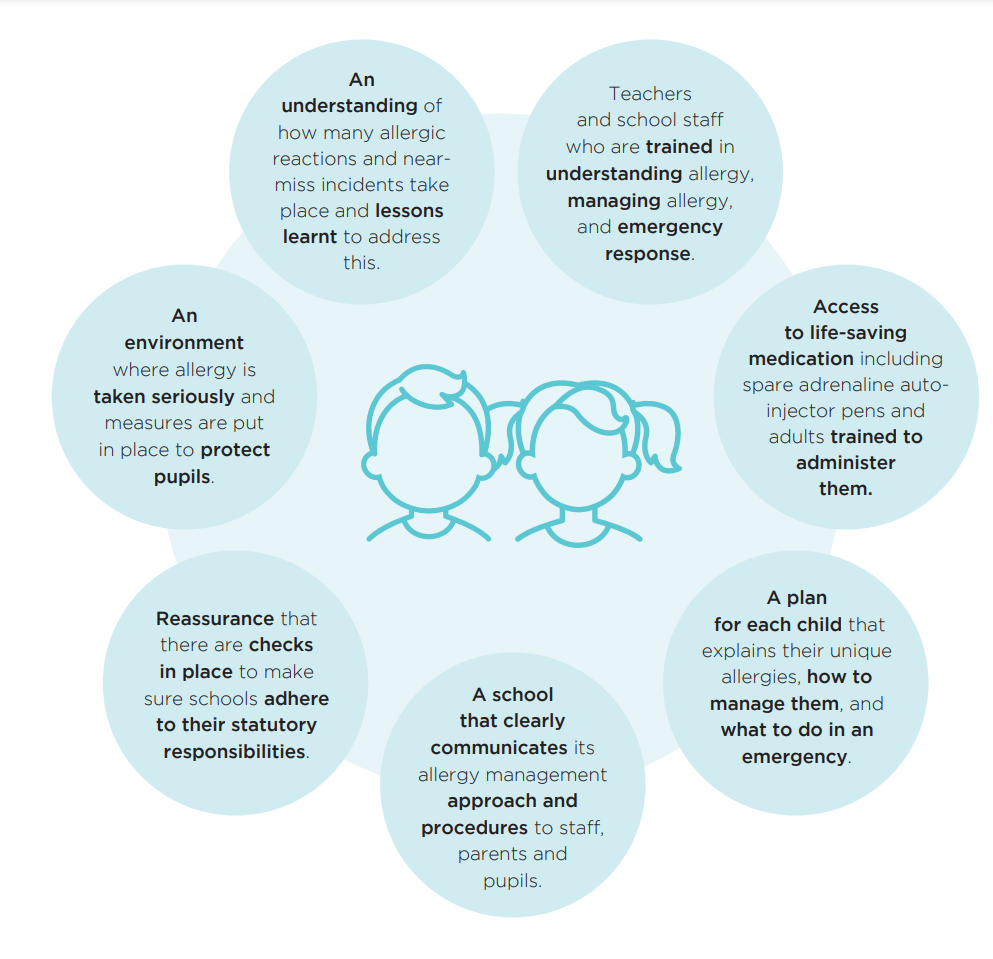
School Allergy Code recommendations

Training

“All schools that are OFSTED monitored AND provide early years education must have at least one member of staff paediatric first aid trained including anaphylaxis treatment”.

First aid training, and even anaphylaxis training, is not the same as allergy awareness, however. 25% of schools don’t train staff on identifying allergy symptoms and anaphylaxis, and what to do in an emergency. Mandatory in New York day care (Elijah’s law), Canadian schools (Sabrina’s law).

Various free and paid for training programmes available. KITT Medical includes training in its package, that includes emergency adrenaline autoinjectors. Natasha Allergy Research Foundation offers Allergy School – includes self assessment for primary schools (also for clubs). Free. Resources for age groups eg 5-7 including going to a party (Armadillo film), assembly plan, top 14 allergen poster.

School Allergy Policy

BSACI Model policy includes (last 9 pages actual template – mostly repetition of initial text): 

  • reference to laws on supporting pupils with medical conditions; 
  • how first aid falls under health and safety policy (designated first aiders)
  • Anaphylaxis management
  • SPare pens in schools
  • Allergy action plans
  • Staff allergy training (says “all staff”, annually) incl risk reduction (no detail), asthma
  • Bullying
  • Storage of medicines, expiry dates
  • Catering – staff must be able to identify pupils with allergies; menus should be available (with ingredients); may contain; [cross contamination is a heading but nothing further]
  • Ana UK safer schools programme and allergyWise training; 
  • Working with parents – must keep school updated, provide medicines and allergy plans.
  • Links to Wiltshire anaphylaxis risk assessment template
  • Sports (in/out school)
  • Insect stings (v brief)
  • Checklist (11 points)

Individual Healthcare Plan

The need for an individual healthcare plan and the medical detail of such a plan should only be assessed by an appropriate designated health practitioner. May include:

  • details of any diagnosed condition or symptoms;
  • the impact that the condition or symptoms has to the individual;
  • details of any medication, dosage, side effects and storage information;
  • special requirements e.g. dietary needs, pre-activity precautions, access to facilities and other reasonable adjustments etc.;
  • what to do, and who to contact, in an emergency;
  • training needs for the support, how often these should be reviewed and who will deliver the training;
  • consent;
  • how often and when the plan should be reviewed;
  • consideration of existing emergency plans, such as Anticipatory Care Plans.

Onion and garlic allergy

Alliums, as are leeks, shallots and chives. Part of same bigger family as asparagus but probably not co-sensitivity.

The main issue with onion is the chemicals released from cut surfaces, which can trigger eye/nose reactions and potentially asthma. But there’s actually some evidence that onion has an anti-allergy action.

With garlic, there is a well recognised contact dermatitis relating to chopping it.

Otherwise, allergy is very rare. Potentially part of celery-spice-mugwort syndrome.

As with that syndrome, the problem for the allergic person is that not only is it not one of the 14 UK recognised allergens for food labelling and restaurants, but it can be included under “spices” if less than 2% of the overall product, without further detail.

Food allergy

Mixed up with “intolerance” and “sensitivity” – intolerance is a vague term for any kind of reaction, agnostic to cause (most commonly used for gastrointestinal symptoms); “sensitisation” has a specific meaning (see allergy diagnosis) so not to be confused. Allergy is where there is an immune mediated problem (based ideally on history and testing) – but sometimes hard to know the mechanism.

2 basic types of food allergy, you can have both at the same time – type 1 (IgE mediated), and non-type 1 (non-IgE mediated – possibly type 4 hypersensitivity).

Most commonly (in Scotland – but varies across UK, especially with different ethnic groups), and varies widely across the world):

  • Milk
  • Egg
  • Peanut
  • Tree nuts
  • Legumes/Pulses
  • Sesame
  • Wheat
  • Crustaceans/molluscs
  • Various fruits

Birch pollen sensitization in Northern Europe changes the kinds of allergies you get – cross sensitivity with fruit and nuts (pollen food syndrome) – whereas in the rest of Western Europe you get more fruit and seed allergies based on LPS.

Allergy has increased over recent decades – “hygiene hypothesis” has now been developed further to address entire “exposome“. Eczema increases the risk of food allergies 6-fold, via genetic and environmental factors (esp filaggrin mutations, and IL-4 receptor alpha chain polymorphisms).

Hospital admissions for food allergy in the UK have increased 3 fold over the last 30 years, with the biggest increase in children [BMJ 2021; 372: n251]. In big English study of primary care records, estimated incidence of probable food allergy doubled between 2008 and 2018; prevalence highest in children under 5 years (4·0%). Rate in children aged 5–9 years 2·4%, 15-19 years 1·7%. In those with previous food anaphylaxis, only 64∙0% of children and young people had at least one prescription for adrenaline autoinjector, and only 50.3% had them on repeat. Adrenaline autoinjectors prescription was less common in those resident in more deprived areas. 93.3% of first health care encounters for children regarding allergy were in primary care, with 2.2% in emergency departments. Only 7.4% of children had been seen for allergy in a hospital clinic. 92.2% of children had only ever been seen for food allergy in primary care (and looking at those prescribed AAIs, 93.5% only ever seen in primary care!).[Lancet Public Health 2024, Paul Turner]

If you ask people about their children’s allergies, up to 28% of infants will report allergies! Lifetime and point prevalence of self-reported food allergy 20% and 13%, respectively – point prevalence of sensitization as assessed by sIgE stands at 17%, skin prick test 6%, and food challenge positivity 1%. Based on clinical history or positive food challenge, food allergies have increased from 2.6% in 2000–2012 to 3.5% in 2012–2021. Point prevalence for under 16s for self reported but physician diagnosed food allergy is 3.75%. Patterns vary across European regions but not in a consistent way. [Spolidoro and Venter 2022]

Having a child with a food allergy has a significant effect on the quality of life for the whole family. One study suggested that having a peanut allergic child had a worse effect on a family than having a child with diabetes, even though with diabetes you also have restrictions on eating and the potential for serious adverse events. A similar study found the same comparing food allergic families with families where a child had a rheumatological diagnosis. The main domains affected were social. Patient/parent feedback pretty consistent across the world however (although most studies done in Europe and English speaking countries), and across time:

  • Parents lived in fear after the first reaction, often perceiving it as traumatic, and often feeling guilt too
  • They tried to live an ordinary family life and had to learn how to be one-step ahead and understand early signs.
  • The family’s social life was also influenced.
  • Parents asked for support and information from health professionals
  • More knowledge and skills increased parents’ confidence (and by implication quality of life – Knibb 2015)

Mothers tend to report greater impact on the child’s quality of life and experience more anxiety and stress than fathers. Mothers tend to shelter the child, whereas fathers more often express a desire to expand their child’s life, and these differences are often greater where parents are separated.

The concern for the child’s safety affected eating outside the home, with birthday parties and visits to peers’ homes particularly threatening. School and nursery are a major source of concern and often led to more parental work, preparing safe lunches.

Parents often felt they had to teach themselves about allergies, due to the lack of early information provided by health care, and then ended up having to teach family, friends and educational institutions too.

Adolescence is a particularly stressful time, as parents recognize the need for the child to become more independent, at the same time that the adolescent can see the parents as excessively controlling (at least with respect to peanut allergy). Supportive friends particularly important for adolescents.

[Larsen Moen, J Ped Nursing 2019]

Moulds

Initial studies did not show any relationship between moulds/damp and health, as there was major confounding with socioeconomic status, and because it is hard to quantify mould exposure (with many different mould species).

Then there is the effect of climate, and the built environment – heating, ventilation, insulation, materials etc.

More recently systemic reviews have made it clear there is a link particularly with development of asthma, particularly in older children, and where there is already a family history of atopy.

Coroner ruled death of 2yr old Awaab Ishak in 2020 from granulomatous tracheobronchitis was due to environmental mould exposure from poor housing.

Longitudinal studies have suggested that there may be protective effects but data is limited.

Similarly there is evidence that higher exposure to moulds leads to more asthma exacerbations.

There are genetic polymorphisms that affect ability to break down the fungal protein chitin, and these have been linked to urgent medical care visits, which suggests a non-immune mechanism may be important.

Dampness is linked to mould growth but also to house dust mite, microbial volatile compounds, mycotoxins and endotoxin.

The most studied mould species are Aspergillus, Penicillium, Alternaria and Cladosporium.

Limited evidence that interventions to reduce mould make any difference.

[European respiratory review 2018]

Muckle-Wells Syndrome

A Cryopyrin disorder, found in Northern Europeans. Cryopyrin triggers an IL-1 dominated inflammatory response, and is coded for by the Cold-Induced Autoinflammatory Syndrome 1 (CIAS1) gene, also known as the NLRP3, NALP3 or PYPAF1 gene.

Attacks of periodic fever are very brief eg 1-2 days – apart from fever, an urticarial rash is sometimes seen, limb pain/arthralgia occurs. Abdominal pain and arthritis occur rarely. Sensorineural hearing loss is characteristic.

Amyloidosis affects 25%, which is high cf other periodic syndromes.

Diagnosis is by genetics.

Steroids are often used but benefit is inconsistent; interleukin 1 (IL-1) receptor antagonist Anakinra shows promise.

Familial cold autoinflammatory syndrome (FCAS) is a similar condition, also related to Cryopyrins. Cold induced obviously, but without the deafness, and amyloidosis is rare.

NOMID/CINCA are also related – the names say it all: Neonatal onset multisystem inflammatory disorder, and chronic infantile neurological cutaneous and articular syndrome. Papilloedema and uveitis potentially leading to blindness occur; there is epiphyseal bone formation; hepatosplenomegaly; and a chronic meningitis with deafness. There is no known treatment, sadly.


Hyper IgD Syndrome (HIDS)

Mostly Dutch and French. Not to be confused with Hyper IgE syndrome or Hyper IgM syndrome. Big database in Nijmegen. A genetic syndrome (autosomal recessive, explained by MVK (mevalonate kinase) gene mutations on chromosome 12p – see Omim) with recurrent febrile attacks starting under 1yr of age.

Attacks last 3-7 days, so may or may not be shorter than TRAPS, occur every 4-8 weeks. Features are:

  • Abdo pain, vomiting and diarrhoea (cf constipation of TRAPS)
  • Headache, arthralgia
  • Swollen cervical lymph nodes – v common, cf TRAPS
  • Splenomegaly
  • Non-destructive arthritis

Diagnosis is by finding of high IgD (>100U/ml); most also have high IgA (with or without raised IgG and IgM), which is an important clue.

Increased Mevalonic acid in urine during fever.

Febrile attacks in response to immunizations often reported, so may be another clue.

Attacks tend to diminish with age without completely disappearing; amyloidosis seems to occur only rarely (cf TRAPS). Simvastatin is supposed to help!


Familial Hibernian fever/TRAPS

First described in a family of Irish descent, hence “Hibernian”, now called TRAPS (TNF receptor assoc periodic syndrome), and now described in a wide range of different ethnicities.

Various mutations of TNF-Receptor Super Family 1A (TNFSF1A) seen, on chromosome 12p (same as HIDS but different gene). These mutations are dominant and penetrate poorly, with only a small proportion developing disease.

Onset is typically around 3yrs of age but varies widely. Periodicity also varies widely: typically every 5-6 weeks. Fever for 3 days heralds onset of other symptoms, which then last for usually 5 days or more (cf Familial Mediterranean Fever):

  • centrifugal migratory erythematous rash, often starting as a patch overlying an area of myalgia, but lots of variation
  • Myalgia – quite striking cf HIDS, uniquely can involve face and neck. CK etc are normal, so due to fasciitis not myositis.
  • Arthralgia – but arthritis uncommon, and non-destructive.
  • Abdo pain is extremely common, often with constipation but may progress to bowel obstruction. Many patients have a history of bowel surgery.
  • Eye involvement is characteristic – conjunctivitis, periorbital oedema; uveitis has been described rarely. cf Behcet’s
  • Pleuritis can occur, but chest pain is more usually musculoskeletal.
  • Lymphadenopathy is rarely very prominent, cf HIDS.

About 14% develop amyloidosis.

Diagnosis is mainly clinical. Must have at least 6/12 history of recurrent inflammatory symptoms, with at least one of the above features, episodes must last at least 5/7 on average (even if variable), with response to steroids but not colchicine. Other affected family members will obviously increase your suspicion. Ethnic group does not seem to have any bearing.

Steroids reduce severity but not frequency of attacks. NSAIDS help fever. Etanercept appears to prevent; colchicine does not (hence one of the diagnostic criteria above!). 

[Medicine 2002;81(5):349-68 PMID 12352631]


Familial Mediterranean Fever

Short attacks of fever, usually lasting 1-3 days, recurring at varying intervals (periodic), cf Behcet’s.

Most children develop severe abdominal pain with the episodes, due to sterile peritonitis.

Pleuritis, leading to chest pain, arthritis, myalgia and skin rashes may also occur.

Most cases are from Arabic Turkish, Armenian or Jewish background. Inheritance is autosomal recessive. The gene has been cloned and four mutations have been identified.

Colchicine is the treatment of choice. Some patients may develop amyloidosis; certain mutations are at higher risk.


Behcet’s syndrome

Recurrent fever and aphthous stomatitis, mostly. However, there is no regular periodicity of the symptoms, and episodes of fever may last for weeks.

Traditionally associated with Mediterranean or Eurasia but in UK mostly white Caucasian.

Other features –

  • arthritis,
  • genital ulcers,
  • iridocyclitis and optic neuritis, even blindness
  • skin rashes (classically erythema nodosum or pustulosis),
  • disabling vascular (thrombosis, superficial phlebitis) and central nervous system complications may occur.

BPSU study found 1 case every 2 weeks in the UK. Median age of onset was 6yrs – but diagnosis 11yrs!

Colchicine as regular preventive treatment, else immunosuppressive treatment. Topical steroids or short courses oral steroids.

PFAPA

=periodic fever, aphthous stomatitis, pharyngitis, adenitis.

Fever every 4-6 weeks (periodic). Neutrophil count normal, cf cyclical neutropenia.

Besides mouth ulcers, sore throat and cervical lymphadenopathy, headache, musty smell (!), abdo pain.

Affected children continue to grow normally, are well between attacks, and do not suffer long-term sequelae.

Treatment with steroids or with cimetidine has been effective, and some children have had no further attacks following tonsillectomy (which suggests some relationship with strep infection but not clear).