Abnormal renal excretion, leading to low potassium.
Presents in early childhood with failure to thrive. Could also be constipation, muscle cramps and weakness (potassium needed for membrane potential, so these are all neuromuscular) and non-specific dizziness and fatigue.
Characteristic hypokalemic, hypochloremic metabolic alkalosis. High plasma renin activity and high aldosterone concentration seen.
Gitelman syndrome is similar, less severe (distal tubule, rather than ascending limb of loop of Henle) – less failure to thrive, in fact often asymptomatic detected incidentally. Might present with nocturia/polyuria.
Urinary calcium excretion distinguishes the two syndromes. Bartter’s waste calcium (more severe, after all), Gitelman retain.
Treatment is with supplementation.
Decompensation can be precipitated by diarrhoea or vomiting. Acute treatment can include potassium-sparing diuretics (spironolactone), cyclo-oxygenase inhibitors and renin-angiotensin blockers.
Symptoms depend on severity and how rapidly decrease has happened. Chronic low levels are better tolerated. Since potassium important for membrane potentials, effects are mostly neuromuscular.
Cramps, weakness, paralysis
Ileus
Metabolic acidosis (although underlying cause often produces alkalosis)
Arrhythmia, heart failure
Rhabdomyolysis
ECG classically shows U waves, T wave flattening, and ST-segment changes. Can be tall wide P waves, can look like long QT if T and U waves merge.
Proteins responsible for a minority of allergic reactions to peanut, hazelnut, sesame among others – hydrophobic, so tend not to be well represented in skin prick and IgE test solutions. May explain false negatives.
Specific IgE tests have been developed, but otherwise you just have to challenge.
Dutch study however didn’t find that specific testing for oleosins helped much.
FMR1 gene is on X chromosome, obviously, and is a trinucleotide repeat disorder (along with Friedrich’s ataxia, myotonic dystrophy, Huntington disease etc), so inheritance is interesting.
Dads can carry gene, but only pass it on to their daughters (who will all get it).
Mums will carry gene on 1 chromosome, so sons and daughters can both get it, but 50:50 chance.
As with other trinucleotide repeat disorders, gene expands with each generation, so risk of disease increases from 1 generation to the next, and this is somewhat predictable: intermediate gene (so 45-54 copies) won’t expand to cause disease (200+ copies) in 1 generation, but premutation gene (55-199) copies probably will.
Features:
Moderately severe learning disability
Facial features – long face, midface hypoplasia, large lips and jaw, small ears
Neural crest tumours – cells that migrate to form sympathetic chain, including adrenal glands.
Usually young children, usually already metastases at presentation – that’s because mostly vague symptoms until an abdominal mass or lymphadenopathy obvious.
Several eye related symptoms possible –
Dancing eyes (opsoclonus-myoclonus) a famous association – only seen in 1% of neuroblastoma but 1/3 of opsoclonus-myclonus syndrome (includes ataxia too!) have it.
Horner’s syndrome associated, as sympathetics (dilated pupil) run with oculomotor nerve.
“Panda eyes” are a rare clinical finding – proptosis, bruising – from orbital mets.
Catecholamines are a marker but only rarely do you get symptoms eg hypertension, sweating, diarrhoea.
Bone pain and fever are not uncommon. Otherwise depends were the mass effects are eg obstructive jaundice, dysphagia.
Investigations
GD-2 marker. Catecholamines as above.
MRI full body else MIBG scintigraphy.
“Metastatic special” risk category – under 18 months, only skin, liver, marrow. Resolve spontaneously even when extensive!
Screening programmes in Germany and US doubled pick up rate but no change in mortality… Probably because detected more of these Metastatic special cases.
WHO 2019 definition – occupational experience characterized by:
Exhaustion (feelings of energy depletion)
Cynicism – increased mental distance from one’s job, or feelings of negativism related to one’s job
Reduced professional efficacy
The MBI-Human Services Survey (MBI-HSS) was published, followed by other versions, including one for teachers and one for medical personnel (MBI-MP). Gives scores for each of the 3 fields. No cut offs, just a continuum, although higher scores across all 3 would clearly fit with the WHO definition.
Attempts have been made to use the tool to then define or screen for burnout. But WHO never called it a disease or disorder, but “a legitimate occupational experience”.
Better to talk about the actual feelings – Overextended, Ineffective, Disengaged – cf Engaged – high scores across all 3 fields.
Organizations should not use the MBI in isolation. Other tools exist such as Areas of Worklife Survey (AWS), which looks at workplace culture in terms of workload, control, reward, community, fairness, values.
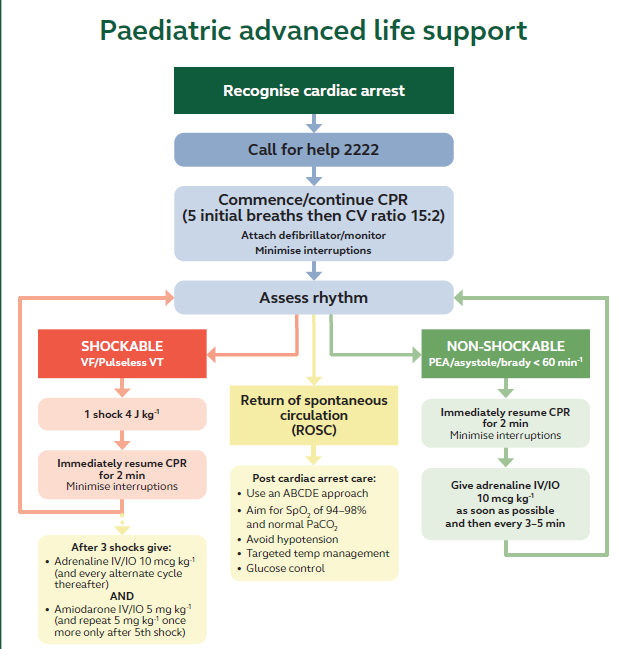
Atropine not part of guideline – neonates 10mcg/kg (no minimum). Else 20mcg/kg min 100mcg.
Out of hospital – Shout for help AND ask for an AED. Sudden OOH collapse likely to be cardiac, even in a child – don’t wait till after rescuer breaths!
Compressions 100-120.min for both infants and children. One third depth of chest – 4cm infant, 5 child (6 adult). 1 finger breadth above xiphisternum to avoid organs.
40% blood volume might be lost before hypotension appears…
5th centile for systolic BP is 70 at 1yr, 80 at 10, 90 at 15yr.
Haemothorax might be picked up in B but don’t manage until C!
C – compartments of body incl long bones. 1:1 RCC:FFP
TXA – bolus, remember 2nd dose (or double bolus).
Log roll can be missed if suspected spinal unless penetrating back wound suspected (or found on absorbent surface…)
It therefore joins beneficence, non-maleficence and respect for autonomy as one of the cardinal principles (Beauchamp and Childress).
What fairness means is debatable, however. And these different principles can conflict.
But it still has value as a way of analysing ethical problems. Hopefully in advance of the problem becoming real for someone.
Aristotle’s theory of justice or fairness is a good place to start – “equals should be treated equally” is straightforward, but it also includes “unequals should be treated unequally, in proportion to their inequalities). In other words, some people may need to be treated differently (“unequally”) because they need the treatment more.
Once a child starts school/nursery, the risk of reactions (and anxiety about potential reactions) starts to ramp up. Obviously, this is because other people are responsible for sourcing and providing food, often to many different children at once.
In the UK, probably 1 pupil with a food allergy in every classroom.
“Schools are the most common setting for severe allergic reactions, with 18% of all food allergy reactions and 25% of first-time anaphylactic episodes occurring there. Fatal anaphylaxis in children occurs more often in schools than any other setting” [Benedict Blythe Foundation “Keeping the promise” document] – but this data appears to be from old US studies. From my data (19/8/26) I see 4 mentions of anaphylaxis related to school in the last 2 years (about 10% of all anaphylaxis reports) – but half of these were actually related to after school.
Miranda Crilley (CHI Dublin) reported on 521 food allergic children attending school/nursery, and found a 4.5/5% annual rate of reactions in schools. Half of nursery reactions due to milk. 6 of 7 nut reactions in schools with nut bans! 33% of children had not provided copies of their allergy action plans to the school. 22% or the reactions were judged as anaphylaxis, none received adrenaline from school staff. “Promoting milk/egg tolerance in infancy would prevent”.
Scottish government policy on healthcare needs in schools (2017): talks about “coordinated support plans” as well as individual health plans and child plans. Talks about local strategic joint arrangements between NHS boards and educational authority. Inhalers and defibrillators (!) specified. “General awareness raising training of common conditions should be provided… for example, asthma, diabetes, epilepsy, eczema and allergic reactions (including anaphylaxis).”
Specific school arrangements may include:
who in the school accepts responsibility, in principle, for supporting the healthcare needs of children and young people in the school;
who is responsible in school for staff training in regard to supporting healthcare needs and administering medication;
emergency procedures at the school including a main point of contact in the school health team [defined how?];
details of any centrally held inhalers; anaphylaxis auto-injectors; the storage of and access to medication in the school;
who is responsible for ensuring the safety of children and young people’s self-management of their medical conditions;
the arrangements in place to ensure that staff are informed and kept up to date about children and young people’s healthcare needs at school.
First do no harm – parents tend to overestimate risk of anaphylaxis, whereas there are clear consequences to restricting the child’s ability to sit with other children at snack/meal times, or restricting the food choices of other children.
Recommends that an Allergy management policy should be in place (even if incorporated into wider medical conditions policy) even if no currently diagnosed allergic children [quotes 25% undiagnosed reaction rate in school] – cites 2017 Government supporting CYP with healthcare needs document:
Procedure for identifying pupils with allergy and high risk pupils.
Details on developing Individual Healthcare Plans.
Protocol for storage and access to emergency medication – emergency kits.*
Arrangements for staff training.
Policies and arrangements on Preventative Measures.
Details on the administration of medications.
Protocol for the emergency response to anaphylaxis.
The rights, roles and responsibilities of staff, pupil(s) and parent/ carer(s).
Highlights breakfast clubs and after school as under the remit of schools (and school trips, too).
And another about how schools can become more allergy aware – because it’s not just about nuts – https://youtu.be/JHnmcmUP6Cs?si=FgjhoxcOdMoEb7eS. George Raptis has shown how school allergy training (in NW England) can improve allergy awareness, not just confidence in managing an allergic emergency.
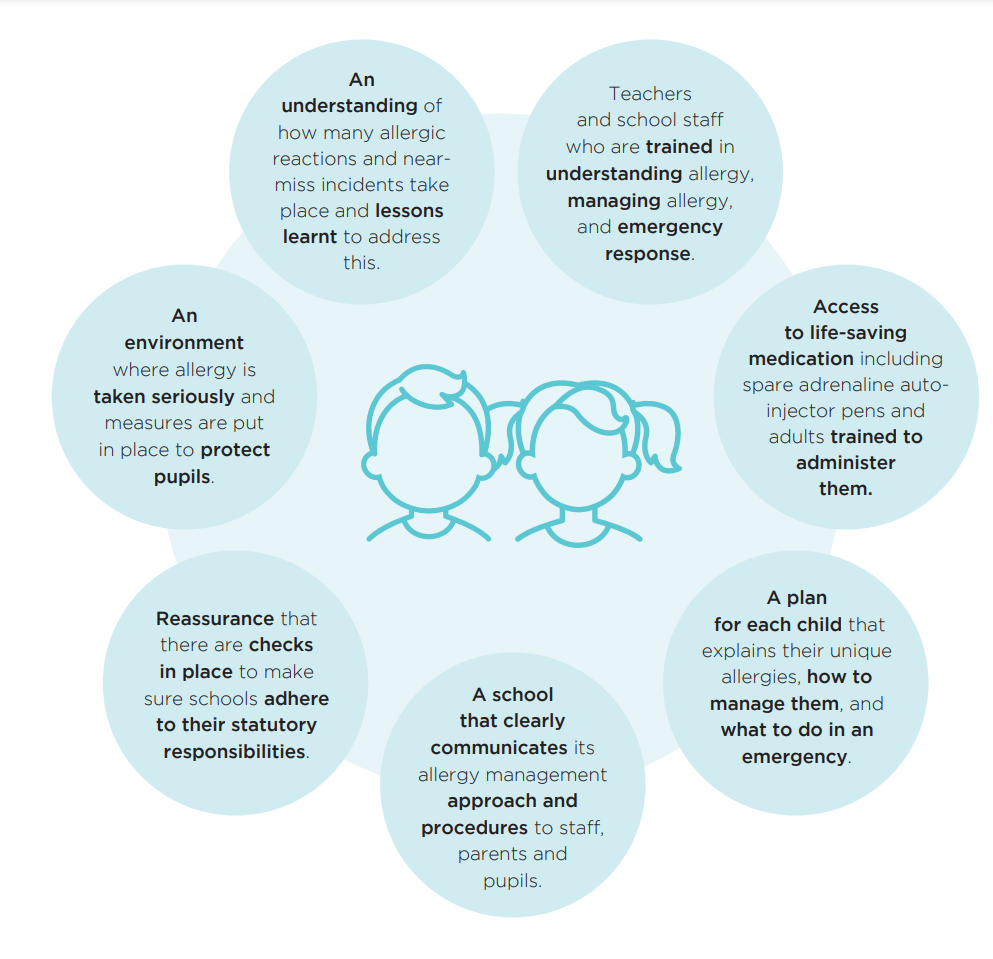
Whole school approach – not just catering/medical – skills (risk reduction, inclusion, first aid); allergy awareness in classroom activities [curriculum?]
Communicate clearly – Allergy and Anaphylaxis Policy (no template!) – (accessible), – and designated allergy lead. IHPs (individual health plans)
Clear governance and risk management – designated lead, other roles/responsibilities. Allergies in every risk assessment
Readiness to respond – 2 in date AAIs for those prescribed them. Hold spare pens in obvious place. Annual risk reduction and ana training. “Ana emergency response plan” [in allergy policy, presumably?], rehearse
Schools allergy code backed by Dept of Education in England.
React report
Data from 2000 English schools, about 10%.
Assessed 4 allergy safe guards: a specific allergy policy, spare pens, allergy training for staff, incident reporting.
69% did not have all recommended safe guards in place. “Pot luck whether your local school has medication, communication and education relating to allergy made available to teachers”. But commented on how well schools are managing despite “seeming lack of guidance, training and funding from government”.
School Allergy Code recommendations
Training
“All schools that are OFSTED monitored AND provide early years education must have at least one member of staff paediatric first aid trained including anaphylaxis treatment”.
First aid training, and even anaphylaxis training, is not the same as allergy awareness, however. 25% of schools don’t train staff on identifying allergy symptoms and anaphylaxis, and what to do in an emergency. Mandatory in New York day care (Elijah’s law), Canadian schools (Sabrina’s law).
Various free and paid for training programmes available. KITT Medical includes training in its package, that includes emergency adrenaline autoinjectors. Natasha Allergy Research Foundation offers Allergy School – includes self assessment for primary schools (also for clubs). Free. Resources for age groups eg 5-7 including going to a party (Armadillo film), assembly plan, top 14 allergen poster.
School Allergy Policy
BSACI Model policy includes (last 9 pages actual template – mostly repetition of initial text):
reference to laws on supporting pupils with medical conditions;
how first aid falls under health and safety policy (designated first aiders)
Anaphylaxis management
SPare pens in schools
Allergy action plans
Staff allergy training (says “all staff”, annually) incl risk reduction (no detail), asthma
Bullying
Storage of medicines, expiry dates
Catering – staff must be able to identify pupils with allergies; menus should be available (with ingredients); may contain; [cross contamination is a heading but nothing further]
Ana UK safer schools programme and allergyWise training;
Working with parents – must keep school updated, provide medicines and allergy plans.
Links to Wiltshire anaphylaxis risk assessment template
Sports (in/out school)
Insect stings (v brief)
Checklist (11 points)
Individual Healthcare Plan
The need for an individual healthcare plan and the medical detail of such a plan should only be assessed by an appropriate designated health practitioner. May include:
details of any diagnosed condition or symptoms;
the impact that the condition or symptoms has to the individual;
details of any medication, dosage, side effects and storage information;
special requirements e.g. dietary needs, pre-activity precautions, access to facilities and other reasonable adjustments etc.;
what to do, and who to contact, in an emergency;
training needs for the support, how often these should be reviewed and who will deliver the training;
consent;
how often and when the plan should be reviewed;
consideration of existing emergency plans, such as Anticipatory Care Plans.