All posts by admin

Sleep-related hypermotor epilepsy

Onset around age 9.

Can be just waking up, possibly confused, but multiple times a night.

Easier to diagnose if more dramatic twisting, grimacing, thrusting movements, posturing. Can be wandering like parasomnia, can be vocalisations (screaming, moaning, crying).

Can be aware during seizure. Can be sensation of unable to catch breath.

Usually around 30 secs.

Often inherited (prev called autosomal dominant frontal lobe epilepsy). Not always frontal!

Probably needs video EEG.

See also Panayiotopoulos (occipital lobe) epilepsy.

Mast cell activation syndrome

Recurrent mast cell degranulation causing episodes of hives, diarrhoea, swelling, dizziness, even anaphylaxis.

Thought to be due to clonal expansion of abnormal mast cells, not requiring usual triggers.

Diagnosis is on basis of rise in tryptase levels during an episode from base line. If base line tryptase is abnormal, then likely mastocytosis.

Look for KIT D816V on flow cytometry? Urine mast cell products eg leukotriene, prostaglandin? Bone marrow aspiration?

Scoring systems available.

Treatment is predictably:

  • Antihistamines, preferably non sedating. Some people however benefit from the additional sedative effect of older antihistamines eg ketotifen, hydroxyzine.
  • Adrenaline autoinjectors for anaphylaxis self management
  • Montelukast/zafirlukast has systemic anti-inflammatory action
  • Famotidine has anti-histamine action
  • Steroids for short term use
  • Omalizumab

Citrus allergy

Orange, mandarin, tangerine all varieties of orange. Seeds probably rich in allergens but less likely to be eaten (chewing probably also required for reaction)!

Various allergens identified, including profilin (so oral allergy syndrome) and LTP (more in Mediterranean, cross reacts with Pru p3, not surprisingly).

One letter briefly touches on citrus cross reactivity – some tolerate lemon and/or tangerine, some had oral symptoms with tangerine, none had tried grapefruit. So varying and not well explored…

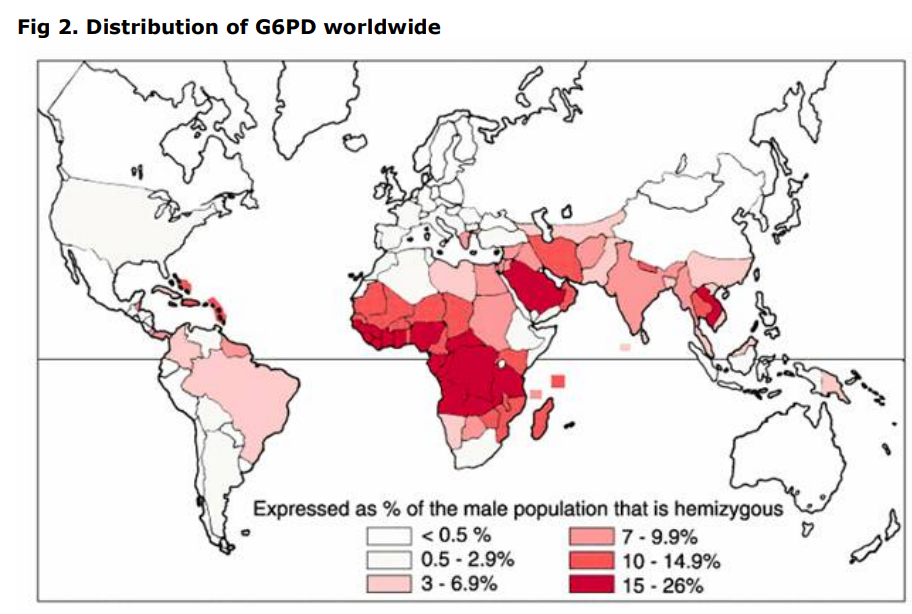
G6PD deficiency

Glucose 6 phosphate dehydrogenase deficiency. X-linked.

Can present with prolonged jaundice in babies. Otherwise with haemolysis (causing jaundice and anaemia).

Haemolysis triggered by infections, but also drugs and chemicals. Classically sulfonamides, but most relevant are:

  • Anti-malarials (ironically)
  • Nitrofurantoin!
  • Aspirin (so Kawasaki)
  • Henna! Other dyes
  • Moth balls!

Geographical risk areas –

Liminality

Liminality in medicine is the idea that you can be between illness and wellness.

Paul Turner et al give the example of having a food allergy: people with allergies do not consider themselves fully ‘ill’ or entirely ‘well’, but something in between. They are typically “well” so long as they apply food safety skills to avoid their trigger food(s) – but a slip or mistake can lead to a reaction and potentially death from anaphylaxis.

With liminality, a young person feels set apart, or a family feels their child is different from others – this can impact on self image, social interaction, which in turn can lead to denial or other unhealthy coping strategies and adverse health outcomes.

[Sanders, Soc Sci Med 2019]

Air transmission

Aerosol and droplet transmission are no longer in fashion – to be replaced by single term “air transmission”.

Similarly, no longer a list of defined “aerosol generating procedures” – flowchart to come that looks at whether coughing is induced and whether “high speed device” used.

[First letter from new Public Services Delivery body?!]

Non traditional medicine and alternative health beliefs

Non-disclosure of use of traditional, complementary and/or alternative medicine (TCAM) is found in 20 to 77% of studies. This has been attributed to an anticipated negative or dismissive response; assumption that health care professionals lack knowledge on the subject; or the HCP not asking.

HCPs who take the time to listen attentively and respectfully are more likely to have patients disclose TCAM use.

Some cultures/religions are more likely to use TCAM, and are also more likely to suffer from heath inequalities and stigma. If seen as ‘alternative’ and contrary to mainstream medicine, discussion might be perceived by both patient and doctor as irrelevant. If perceived within a more ‘integrative’ framework, it is more likely that TCAM use will be a topic for discussion. The transition from a “traditional-alternative” to a “traditional-integrative” approach to care is being promoted by the World Health Organization’s Traditional Medicine Strategy (2014–2023).

Tangkiatkumjai et al. suggested that TCAM use can be accompanied by an expectation of benefit; perception of safety; and dissatisfaction with conventional medicine. Perception of safety can of course be very misguided, eg interactions between herbal products and cancer drugs.

In oncology, integrative programs focus on quality of life-related concerns, eg chemotherapy-induced peripheral neuropathy, preoperative anxiety and postoperative pain. These programs have been shown to increase patient adherence to oncology treatment regimens, within a safe and effective environment.

Patient trust in their HCP has been shown to increase when asked directly about TCAM use.

Try the LEARN (Listen, Explain, Acknowledge, Recommend, and Negotiate) model, proposed by Berlin and Fowkes.

Non-judgmental approach essential – stereotypes, prejudices, and misconceptions may compromise the therapeutic relationship.

Other family/community voices that can be included?

“What are your goals of treatment with TCAM? Is your primarily goal to relieve your symptoms and improve your quality of life? Or is it to “fight” or cure the disease, prolong life, “strengthen” your immune system, or another goal?”

[Humility about failures/faults of conventional medicine!]

[Ben-Arye, 2024]
Clinic Letters

2026 updated guidance from Academy of Royal Medical Colleges “Please write to me” – highlights frequent complaints about poor communication in the NHS, how communication issues will disproportionately affect people with lower levels of health literacy. Now includes discharge summaries.

  • No nasty surprises – should repeat and add information but not give new or upsetting information
  • Tailored to individual patient – record patient preferences about how they can best read/process
  • Include questions asked by patient and GP, and answers
  • Explanation of new or changed treatments
  • Problem/diagnosis list is optional!
  • Section aimed directly at GP optional
  • Links to other sources of information and decision aids should ideally be from Patient information forum “Trusted information creator database”
  • Break up text with paragraphs and bullet points
  • Aim for Flesch reading ease score of 70 or above (UK reading age 9-11)
  • Provide technical information in short sentences

2020 interview study with GPs in the Midlands –

Giving letters to patients has benefits of a sense of patient inclusion, increased patient understanding, patient autonomy, enhanced communication transparency. The letter can act as a memory-aid (for example, medication). Paper-held summary may also act as a physical record of the admission for future encounters and communications, particularly if the patient sees a team who do not have access to the letter (for example, out-of-hours GP).

But if discharge letter is no longer simple summary, but exercise in patient education. GP then has to wade through a lot of excess information.

Letter to patient can alarm patients (especially if inaccuracies), language barriers and patient low literacy lead to health inequalities. GP may be asked to explain letters to patients. Ethics of cases where the diagnosis had not been disclosed, confidentiality breaching if the letter contains third-party information or if patient loses the letter. Patient can be upset by sensitive issues (eg, obesity).

Tips therefore include:

  • Give patient choice regarding getting letter (AoRMC says check how they like to be communicated with) – some people are sensitive about information being posted out.
  • Give patient an abbreviated/edited version
  • Include simple interpretations of results (“normal”, “satisfactory”)
  • Insert a patient information section

Common gripes:

  • Hidden Actions: Critical requests (e.g., ordering blood tests or prescribing new drugs) are often buried in paragraphs rather than clearly itemized.
  • Missing Information: Letters frequently omit the specific rationale for medication changes or leave out essential physical measurements or mental health assessments.
  • Jargon and Acronyms: Traditional letters are often written with heavy medical terminology. This confuses patients who then book GP appointments just to have the letter explained.
  • Delays: Administrative backlogs and IT glitches often mean letters arrive too late to safely guide a patient’s ongoing primary care.

What GPs Actually Want:

  • A Dedicated Action Section: GPs overwhelmingly prefer structured letters that feature a bolded “GP Action” or “Please Consider” section at the very beginning or end.
  • Concise Formatting: Because GPs spend less than a minute reading most routine letters, they favor bullet points and standardized headings for diagnoses, management plans, and required investigations.
  • Direct Communication with Patients: Academy of Medical Royal Colleges “Please write to me” guidance promotes writing clinic letters directly to the patient (in plain English) while copying in the GP. This saves GPs time and boosts patient understanding

Shetland improvement project highlights that letters are processed by admin and pharmacy staff and often they need to involve clinical staff or contact the patient themselves to help understand what is being requested of them. Patient feedback included “it helped me understand the journey I was on”, “quite a lot of jargon and medical terms I didn’t understand”, “didn’t feel I needed it as I trust relevant information has been given”.

AI in portfolios

RCPCH guidance –

Using AI safely, effectively and critically is a skill that all doctors need to develop!

Generative AI tools have a significant carbon footprint. 

Doctors are expected to demonstrate their ability to be a reflective practitioner by developing both written and verbal reflection skills. AI should only be considered as a supplement to writing skills and not as a substitute.  

While AI might help with creating an outline for reflection, using AI to create artificial patient encounters or to take a purely mechanistic ‘cut and paste’ approach to ePortfolio entries risks raising concerns surrounding probity.

Educational supervisors should explore reflective ePortfolio entries with their supervisee during supervision meetings and should routinely discuss reflection and encourage verbal reflection, an essential skill for trainees. [esp serious incidents].

Doctors in training should expect to have some of their ePortfolio entries explored by their educational supervisor and/or the ARCP panel. 

Feedback and self-reflection in MSF should not be generated by AI. 

Travel with allergies

Paul Turner’s 2024 review of food allergies and commercial flights –

  • Research (including aircraft simulations) show no evidence to support airborne transmission of nut allergens as a likely phenomenon. Announcements requesting ’nut bans’ are not therefore supported, and may instal a false sense of security.
  • The most effective measure is for passengers to wipe down their seat area (including tray table and
    seat-back entertainment system). Food proteins are often ’sticky’ and adhere to these surfaces, from where they are easily transferred to a person’s hands and onto food that might be consumed. Airline companies can help to facilitate this through pre-boarding.
  • Passengers at risk of anaphylaxis should be prescribed two adrenaline autoinjector devices, to carry on their person at all times—including when flying. Airlines should consider including a separate supply of ’general use’ adrenaline autoinjectors in the onboard medical kit for use in an emergency.
  • All airlines should have clear policies relating to food allergies which are easily available from
    their websites or on request. These policies should be applied consistently by both ground staff and cabin crew, in order to provide reassurance to food-allergic passengers and their caregivers.

[I would say all children with a type 1 food allergy are at risk of anaphylaxis, but I would only prescribe EpiPens for someone at HIGHER risk]